
Patient Dies by Suicide After ‘Insurance Issue’ Delayed Medicine for Lung Disease Flare-Ups

If you or someone you know may be experiencing a mental health crisis, contact the 988 Suicide & Crisis Lifeline by dialing or texting “988.”
KYLE, Texas — Kenney Blewett was diagnosed with lung disease more than a decade ago but started experiencing flare-ups this year that made him feel like he couldn’t breathe.
Blewett described those flare-ups as “the scariest thing in the world,” said his wife, Cindy, adding that while the episodes typically lasted no more than a few minutes, they had become more frequent.
On top of that, simple tasks, like taking out the trash, left Blewett winded. He rarely left the house and had recently lost 45 pounds. “That sounds like cancer,” Cindy remembered one of his doctors said. It was clear, she said, that her husband’s poor health, tied to decades of smoking, was getting worse.
That’s why, on June 2, Blewett’s pulmonologist wrote him a prescription for a new medication to improve the terrifying breathing issues caused by chronic obstructive pulmonary disease, or COPD. But the prescription wasn’t immediately filled. Two days after that doctor appointment, Blewett received an email from Walgreens explaining that, “due to an insurance issue that we’re working to resolve,” the medication was delayed.
“He was hopeful that it would work,” Cindy said of the drug, two months after her husband’s death. “I wish we had the chance to find out.”
Insurance delays and denials have become an infamous feature of the American healthcare system, with nearly 7 in 10 adults calling them “a major problem,” in a January KFF Health Tracking Poll.
In June 2025, six months after UnitedHealthcare’s CEO was shot in New York, the Trump administration announced a highly publicized industry pledge, signed by dozens of major health insurers, to remove some of the barriers that block or delay patients from accessing doctor-recommended care. And yet that pledge was voluntary, and it carries no penalties if companies fail to comply. Indeed, a report published by KFF Health News in July found that some insurers that signed the pledge would not implement all the promised initiatives as originally outlined.
Last year, the Trump administration announced a voluntary pledge by dozens of insurers to improve prior authorization, which often requires patients to seek approval before treatments. But prior authorization remains commonplace, and there’s no evidence the government is trying to hold insurers to account.
In recent years, lawmakers in most states, including Texas, have attempted to address delays and denials by regulating the insurance industry in the absence of substantial federal reform. But most health insurance plans, including traditional Medicare policies and employer-sponsored offerings, which together cover more than half of all Americans, typically aren’t under state jurisdiction.
Even some medical office staff and pharmacy employees find the patchwork of state and federal insurance rules and regulations confusing, a problem that is poised to become more complicated as artificial intelligence plays a larger role in approving and processing claims.
“It’s just gotten completely out of hand,” said Matt Toresco, CEO of Archō, a patient advocacy and consulting company. He argued that patients need more assistance facing insurance hurdles.

The Blewetts’ story illustrates how navigating these complexities remains a herculean task for patients and their caregivers.
Cindy has sought answers from Medicare; Kenney’s private Part D drug plan; his pulmonologist’s office; and Walgreens. She still has questions about who was responsible for the medication delay and how the holdup could have been prevented.
If the COPD flare-up Blewett experienced on the afternoon of Sunday, June 7, could have been avoided, she wondered, would he still have chosen to die by suicide that night?
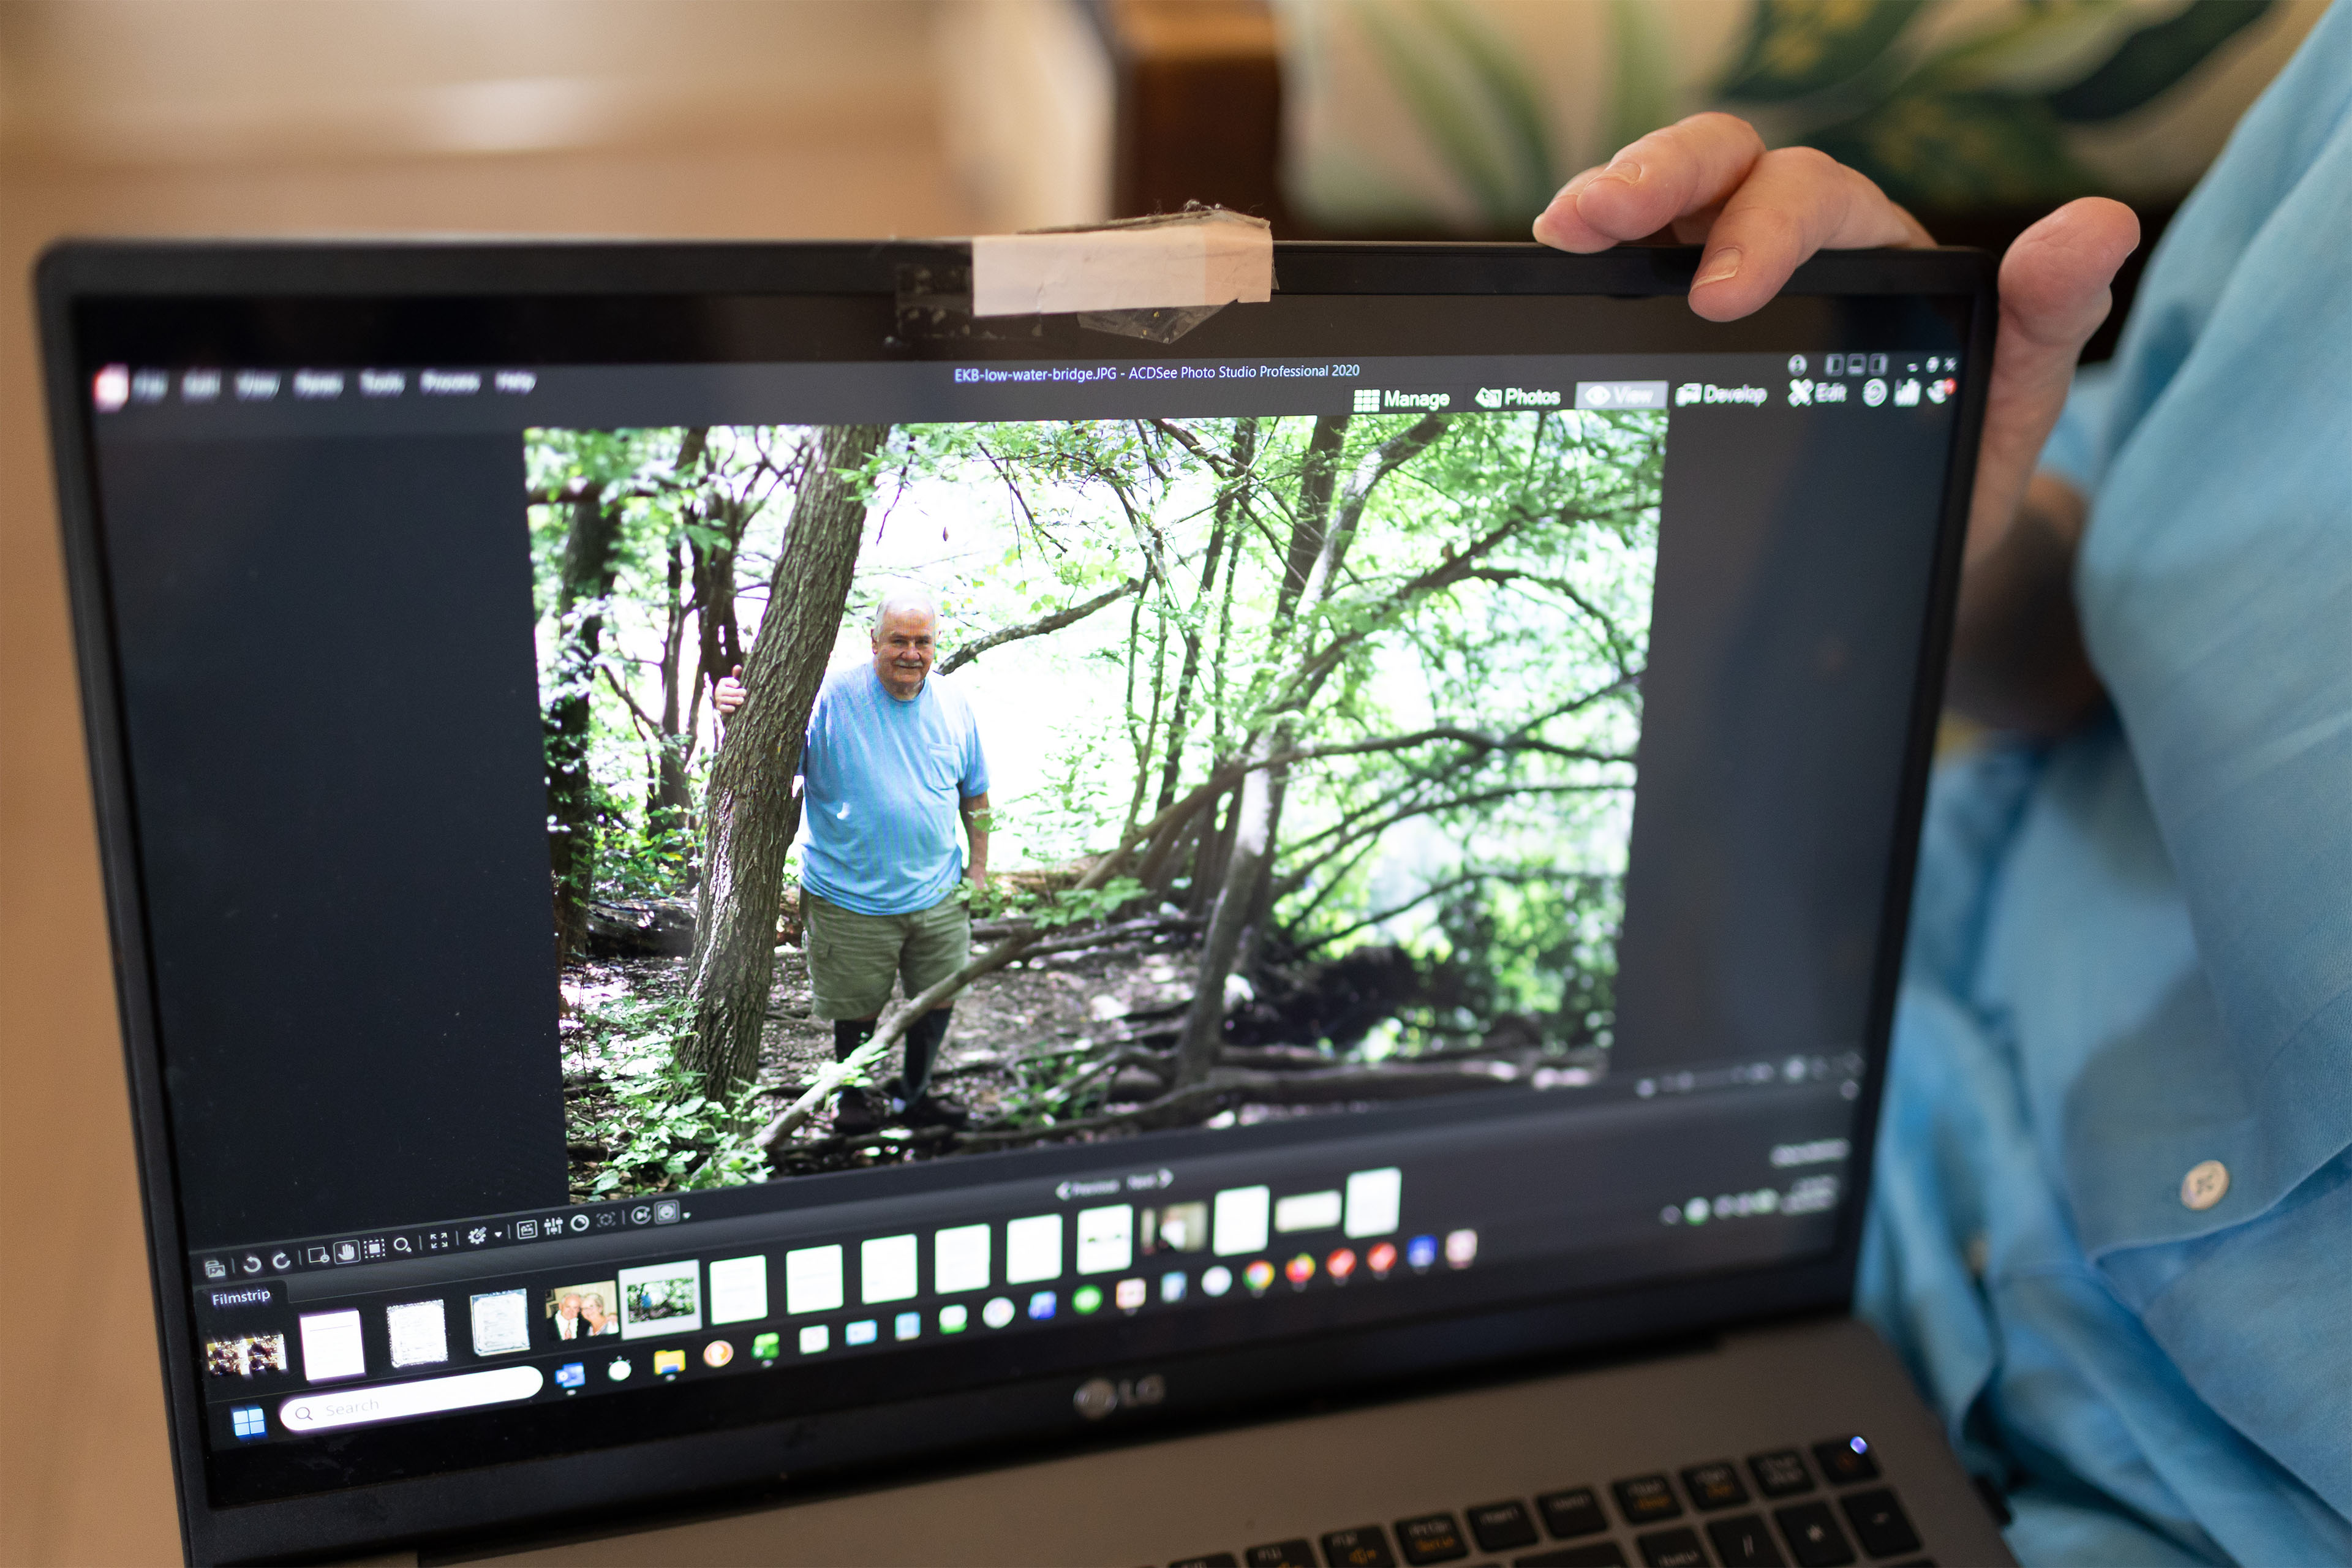
‘Complex and Convoluted’
During that first week of June, Cindy said her husband repeatedly asked if his prescription — a liquid medication meant to be inhaled through the nebulizer machine Kenney owned — was ready to be picked up from Walgreens.
Cindy said she wasn’t initially surprised or worried by the delay. Since its acquisition by a private equity firm last year, Walgreens has cut thousands of jobs across the country, according to the Private Equity Stakeholder Project. Cindy said in August that their Walgreens pharmacy in Kyle seemed to her to have been understaffed for months, and that prescriptions were being filled more slowly.
When Cindy called the pharmacy a few days after Kenney’s appointment to find out more about the insurance delay, she said, a Walgreens employee told her the prescription required prior authorization. Also called preapproval or precertification, prior authorization is a practice widely used by health insurers that requires medical providers to seek permission before their patients may receive covered treatment.
But Cindy didn’t know which of Kenney’s insurers required prior authorization for this medication.
For years, she had helped manage multiple policies on behalf of her husband. Kenney was insured by Medicare parts A and B, the federal health insurance program for people 65 and older or with disabilities. But he also had a private Part D plan to cover drug costs through Wellcare Value Script, as well as a Medicare supplement plan through Blue Cross and Blue Shield of Texas — also called a “Medigap” plan — that paid for other out-of-pocket costs.
Initially, Cindy assumed that Kenney’s Part D plan had invoked prior authorization for his new medication. But because it was a liquid that is inhaled through a nebulizer machine, this drug was one of relatively few covered by Medicare Part B’s durable medical equipment benefit, not Part D.
The federal government had no record showing that this prescription had been billed to Kenney’s Part B policy, the Medicare agency told Cindy over the phone, she said.
Sarah Tanner and Myriea Amaya, spokespeople for Centene, Wellcare Value Script’s parent company, would not answer questions for this article.
After Kenney’s death, when Blewett sought clarification at the Walgreens pharmacy, she said the employee “kept saying different things.” She recalled his explaining that the prescription was submitted to Medicare Part B but without a necessary diagnostic code that the doctor should have included.
Carmen Lopez, a spokesperson for Walgreens, told KFF Health News in late September that the company “cannot comment on matters involving specific individuals.”
Subsequently, Cindy said, a district pharmacy supervisor for Walgreens reached out by phone, and told her the pharmacy tried to process the prescription through Part B on June 2, the same day as the pulmonologist appointment, but that the prescription was missing a diagnostic code from the physician. The supervisor said Walgreens sent a request for that code to the pulmonologist’s office later that day, Cindy recalled.
Kenney’s pulmonologist — Rajesh Shetty of LungDocs — did not respond to phone or email messages from KFF Health News. But Cindy said an employee at the practice told her they did not see a fax from Walgreens asking for a diagnostic code for the prescription.
Meanwhile, it couldn’t have been an issue with Kenney’s Medigap plan, since those policies don’t require prior authorization.
“Short of getting attorneys involved,” Cindy said, “I’m not sure how to find out what really happened.”

More Red Tape Ahead
Confusion surrounding these Part B and Part D distinctions is common, said Mike Hess, senior director of patient outreach and education at the nonprofit COPD Foundation. “Medicare has gotten to be so complex and convoluted over the years,” he said, that even medical office staff and pharmacy employees often misunderstand the nuances.
And with the introduction of AI to the preapproval process, navigating insurance hurdles will likely get more complex for Medicare beneficiaries, doctors say.
Historically, traditional Medicare, unlike Medicare Advantage, used prior authorization sparingly. But in January, Medicare launched a pilot program in six states — Arizona, New Jersey, Ohio, Oklahoma, Texas, and Washington — testing the use of AI to preapprove some healthcare services.
It is intended to “root out waste in Original Medicare,” CMS Administrator Mehmet Oz has said, but physicians and patients say the program is creating more red tape for Medicare beneficiaries and leading to inappropriate denials. The pilot program does not currently impose prior authorization requirements on COPD medications, but industry experts expect the scope of the initiative will grow to include more services and states.
On the night of June 7, hours after her husband’s last COPD flare-up, Cindy Blewett was sitting on their back porch when she heard a loud noise. She assumed a picture had fallen off the wall in the living room. In fact, it was a gunshot. She discovered Kenney’s body in their bedroom.
“I can’t tell you how horrible it was,” Cindy said.
She said her husband had struggled with his mental health for a long time and had attempted suicide once before, years ago. His deteriorating health only made things worse, she said.
Kenney confirmed that much in a note he left. He told Cindy that she was a wonderful wife, mother, and grandmother but that his health was too poor to continue living.

A second COPD medication, which his pulmonologist ordered directly from the drug manufacturer during the June 2 appointment, arrived several weeks after Kenney’s suicide, she said.
“Perhaps, just perhaps,” Cindy said, “if he had received both medications in a timely manner, he would be here today, and we would have had many more years together.”
Do you have an experience with prior authorization you’d like to share? Click here to tell KFF Health News your story.
Source link

